Thyroid, Steroid, Sex Hormone and Bone Drugs for NEET PG Pharmacology: Levothyroxine (ICMR), Antithyroid Drugs, SERMs, Bisphosphonates
Start Here
🎯 Exam priority: High. Expect: levothyroxine starting dose in an elderly cardiac patient, the antithyroid drug in the first trimester, steroid withdrawal, tamoxifen and the endometrium, raloxifene and clots, and how to take alendronate.
CBME mapping: PH 7.3–7.9. Indian protocol: ICMR Hypothyroidism workflow (July 2022).
Hypothyroidism: Levothyroxine (ICMR)
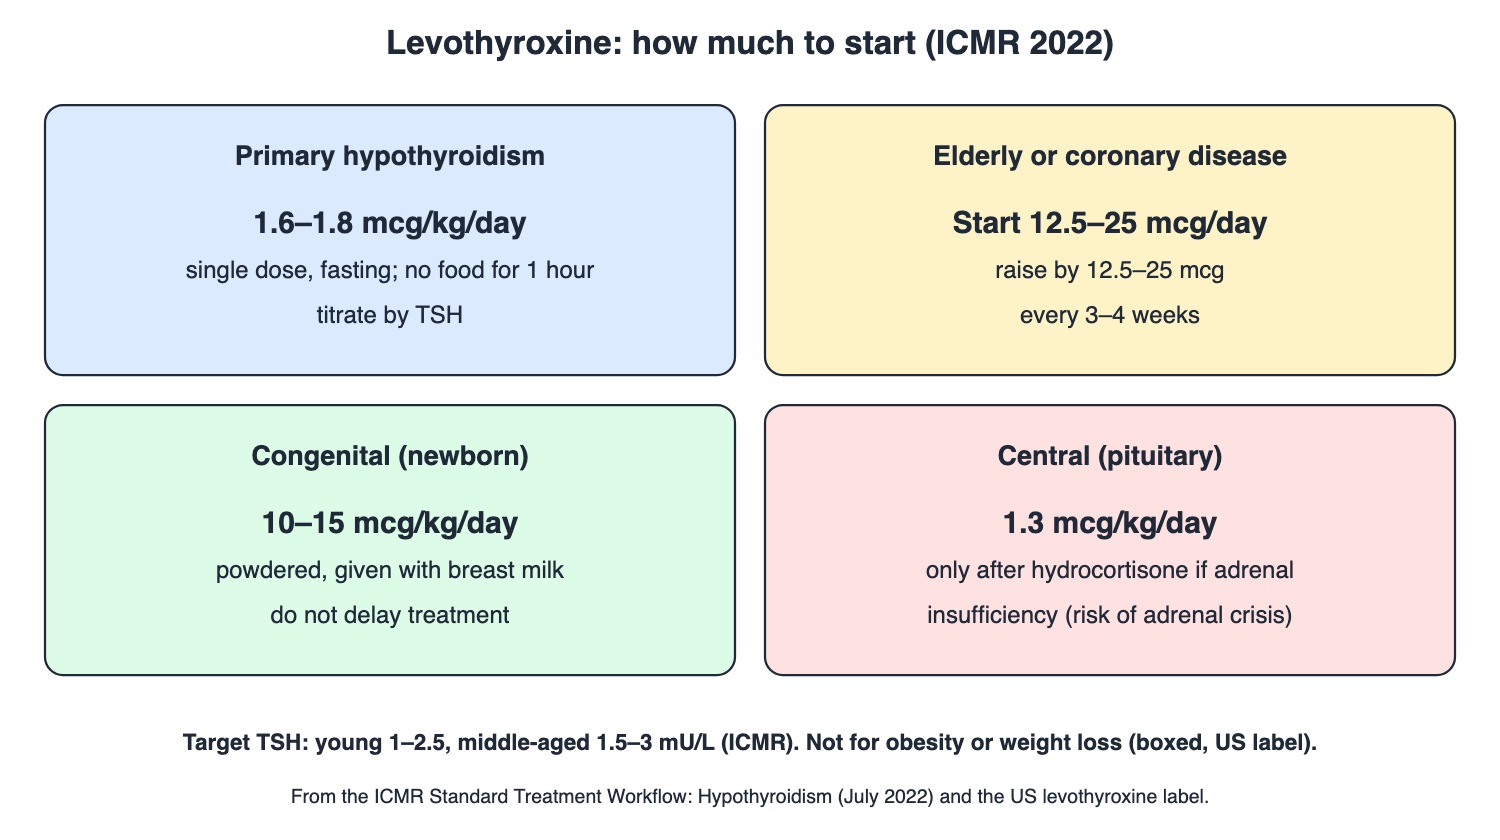
Levothyroxine starting doses by type of hypothyroidism, from the ICMR workflow (2022). Drawn by TrackNation.
Diagnosis: overt = high TSH with low FT4; subclinical = high TSH with normal FT4. Billewicz score ≥ 6 suggests hypothyroidism. Newborn screening: TSH > 30 mU/L.
Take it on an empty stomach, 30–60 minutes before breakfast, and at least 4 hours apart from drugs that block its absorption.
Central hypothyroidism: give hydrocortisone first if there is adrenal insufficiency — thyroxine alone can precipitate an adrenal crisis.
Never use thyroid hormone for obesity or weight loss (boxed warning).
Hyperthyroidism: Antithyroid Drugs
Methimazole: life-threatening agranulocytosis (report sore throat or fever at once); in the first trimester it can cause birth defects such as aplasia cutis and craniofacial malformations.
Propylthiouracil: boxed severe liver injury and liver failure, but it may be the drug of choice during or just before the first trimester.
Corticosteroids
Adrenal insufficiency: hydrocortisone or cortisone is the first choice.
Withdrawal: taper gradually; drug-induced adrenal insufficiency can last months after stopping, so restart steroids during any stress in that period.
Adverse effects: unmasked diabetes, posterior subcapsular cataract, raised eye pressure, osteoporosis, growth suppression in children; no smallpox (live) vaccination while on steroids.
Sex Hormones and Modulators
Drug | Class (label) | Key warning (label) |
Estradiol | Estrogen | Endometrial cancer if unopposed; not for preventing heart disease; probable dementia in women ≥ 65 (WHI) |
Raloxifene | SERM | Boxed: venous thromboembolism and death from stroke |
Tamoxifen | SERM | Uterine malignancies, stroke and pulmonary embolism (in DCIS and risk-reduction use) |
Letrozole | Aromatase inhibitor | Adjuvant treatment of postmenopausal hormone-receptor-positive breast cancer |
Clomiphene | Ovulation inducer | Ovarian hyperstimulation syndrome; visual blurring or flashes |
DMPA (Depo-Provera) | Injectable progestin contraceptive | Boxed: bone mineral density loss; not beyond 2 years unless other methods unsuitable |
Bone: Bisphosphonates and Denosumab
Alendronate: swallow with plain water at least 30 minutes before the first food, drink or medicine of the day, and do not lie down for 30 minutes. Watch for osteonecrosis of the jaw and atypical femur fractures (new thigh or groin pain).
Denosumab: RANKL inhibitor; boxed severe hypocalcaemia in advanced kidney disease (eGFR < 30).
Traps the Examiner Sets
Elderly or cardiac patient: levothyroxine 12.5–25 mcg/day, not full dose.
First trimester: propylthiouracil; methimazole later.
Fever and sore throat on methimazole: check for agranulocytosis.
Tamoxifen raises uterine cancer risk; raloxifene raises clot risk.
Alendronate: upright for 30 minutes, empty stomach.
Memory Hooks & Shortcuts
Shortcuts to lock in this article's numbers and lists. Each one only re-packages facts proven above.
🧠 Old heart, Low start (12.5–25) — levothyroxine in the elderly or cardiac
🧠 Steroids before Thyroxine in central disease — avoid adrenal crisis
🧠 PTU for the Pregnant first Trimester — methimazole causes defects then
🧠 Methimazole: Mind the Marrow — agranulocytosis
🧠 Tamoxifen Troubles the uTerus — uterine malignancy
🧠 Raloxifene Raises clots — VTE
🧠 Fosamax: 30-30 rule — 30 minutes before food, 30 minutes upright
Rapid-Revision Cards
Levothyroxine primary (ICMR)
1.6–1.8 mcg/kg/day, fasting.
Levothyroxine elderly/CAD
12.5–25 mcg/day, +12.5–25 every 3–4 wk.
Congenital hypothyroidism
10–15 mcg/kg/day, powdered with breast milk.
Central hypothyroidism
1.3 mcg/kg/day after hydrocortisone.
Target TSH (ICMR)
Young 1–2.5; middle-aged 1.5–3.
How to take T4
Empty stomach, 30–60 min before breakfast; 4 h from binders.
T4 boxed warning
Not for obesity/weight loss.
Methimazole
Agranulocytosis; 1st-trimester defects (aplasia cutis).
PTU
Boxed liver failure; choice in 1st trimester.
Adrenal insufficiency
Hydrocortisone or cortisone first.
Steroid taper
Gradual; HPA suppression for months.
Steroid eye
Posterior subcapsular cataract; raised IOP.
Steroids and vaccines
No smallpox/live vaccine.
Estrogen
Endometrial cancer (unopposed); not for CVD prevention.
Raloxifene
SERM; VTE, stroke death.
Tamoxifen
Uterine cancer, stroke, PE.
Letrozole
Aromatase inhibitor; HR+ breast cancer.
Clomiphene
OHSS; visual flashes.
DMPA
Bone loss; ≤ 2 years.
Alendronate
Water, 30 min before food, upright 30 min.
Bisphosphonate risks
ONJ, atypical femur fracture.
Denosumab
RANKL; hypocalcaemia in CKD.
Sources
Facts in this article were checked against these documents.
Standard Treatment Workflow: Hypothyroidism — Indian Council of Medical Research / Department of Health Research, MoHFW, July 2022
Prescribing labels: levothyroxine, methimazole, propylthiouracil, prednisone, Solu-Cortef, estradiol, Evista, tamoxifen, Femara, clomiphene, Depo-Provera, Fosamax, Prolia — DailyMed, US National Library of Medicine, current labels, accessed November 2026 (link)
Competency Based Undergraduate Curriculum, Pharmacology (PH 7.3–7.9) — National Medical Commission, 2024
Test Yourself: Practice Questions
Twenty-four questions in NEET PG style, most of them clinical vignettes.
Practice Questions (NEET PG pattern)
Original questions written in the style of the exam: +4 for a correct answer, −1 for a wrong one. Every answer was checked against the sources listed above. NEET PG papers are not published by NBEMS, so these are not past-paper questions.
Q1. A 35-year-old woman, 60 kg, has overt primary hypothyroidism. ICMR's starting levothyroxine dose is about
(a) 10–15 mcg/kg/day
(b) 300 mcg weekly
(c) 1.6–1.8 mcg/kg/day (about 100 mcg)
(d) 12.5 mcg/day
Show answer
Answer: (c) — Primary hypothyroidism: 1.6–1.8 mcg/kg/day as a single fasting dose.
Q2. A 72-year-old with angina is diagnosed with hypothyroidism. ICMR advises starting levothyroxine at
(a) 200 mcg/day
(b) 12.5–25 mcg/day, increased every 3–4 weeks
(c) full replacement at once
(d) only after angioplasty
Show answer
Answer: (b) — Elderly and CAD patients start low and go slow.
Q3. A newborn's screening TSH is high and confirmed. ICMR's levothyroxine dose is
(a) wait until 6 months
(b) 1.3 mcg/kg/day
(c) 10–15 mcg/kg/day, powdered, with breast milk
(d) 25 mcg weekly
Show answer
Answer: (c) — Congenital hypothyroidism: start promptly.
Q4. A woman with a pituitary tumour has low FT4 and a low cortisol. Before levothyroxine, ICMR says to
(a) start hydrocortisone first
(b) nothing else
(c) give methimazole
(d) give radioactive iodine
Show answer
Answer: (a) — Thyroxine alone may precipitate an adrenal crisis.
Q5. A patient takes levothyroxine with breakfast and calcium tablets; TSH stays high. The label advice is to take it
(a) on an empty stomach 30–60 minutes before breakfast, 4 hours apart from interfering drugs
(b) twice weekly
(c) at bedtime with milk
(d) with iron
Show answer
Answer: (a) — Levothyroxine label.
Q6. A slimming clinic prescribes levothyroxine to a euthyroid woman for weight loss. The label's boxed warning says
(a) only with metformin
(b) only for men
(c) thyroid hormone must not be used for obesity or weight loss
(d) this is approved
Show answer
Answer: (c) — Boxed warning.
Q7. A woman with Graves' disease is 6 weeks pregnant. The antithyroid drug of choice now is
(a) methimazole
(b) propylthiouracil
(c) levothyroxine
(d) radioactive iodine
Show answer
Answer: (b) — PTU may be the drug of choice during or just before the first trimester; methimazole can cause birth defects then.
Q8. A baby born to a mother who took methimazole in the first trimester has aplasia cutis. This is
(a) a recognised methimazole first-trimester malformation
(b) a forceps injury
(c) neonatal lupus
(d) unrelated
Show answer
Answer: (a) — Methimazole label.
Q9. Three weeks after starting methimazole, a woman has fever and a sore throat. The priority is to
(a) check a white cell count for agranulocytosis
(b) add PTU
(c) double the dose
(d) start antibiotics only
Show answer
Answer: (a) — Agranulocytosis is potentially life-threatening; patients must report fever or sore throat immediately.
Q10. Propylthiouracil carries a boxed warning for
(a) agranulocytosis only
(b) severe liver injury and liver failure
(c) QT prolongation
(d) lactic acidosis
Show answer
Answer: (b) — Some cases needed transplant or were fatal.
Q11. A man stops prednisone 40 mg abruptly after 3 months and collapses after a minor operation a few weeks later. The cause is
(a) hyperthyroidism
(b) allergy
(c) drug-induced secondary adrenal insufficiency
(d) hyperkalaemia from surgery alone
Show answer
Answer: (c) — Taper gradually; insufficiency can last months, so steroids should be restarted in any stress during that time.
Q12. For replacement in primary adrenal insufficiency, the label's first choice is
(a) dexamethasone
(b) hydrocortisone or cortisone
(c) fludrocortisone alone
(d) prednisone alone
Show answer
Answer: (b) — Synthetic analogues may be added with mineralocorticoids where needed.
Q13. Long-term oral steroids in an asthmatic cause cloudy vision; the lens change typical of steroids is
(a) retinal detachment
(b) anterior polar cataract
(c) posterior subcapsular cataract
(d) nuclear sclerosis
Show answer
Answer: (c) — Steroid ophthalmic effects: posterior subcapsular cataracts, raised intraocular pressure.
Q14. A postmenopausal woman with an intact uterus wants estrogen alone for hot flushes. The boxed warning is
(a) estrogens increase the risk of endometrial cancer
(b) estrogens cause hypoglycaemia
(c) estrogens prevent heart disease
(d) no risk
Show answer
Answer: (a) — Also: not for preventing cardiovascular disease; probable dementia in women ≥ 65 (WHI).
Q15. A woman on raloxifene for osteoporosis develops a swollen painful calf. The label's boxed warning covers
(a) hypercalcaemia
(b) osteonecrosis of jaw
(c) venous thromboembolism (and death from stroke)
(d) agranulocytosis
Show answer
Answer: (c) — Raloxifene is a SERM.
Q16. A woman taking tamoxifen to reduce breast-cancer risk asks about its serious risks. The label lists
(a) uterine malignancies (and stroke, pulmonary embolism)
(b) hypothyroidism
(c) bone loss only
(d) ovarian hyperstimulation
Show answer
Answer: (a) — Serious events in risk-reduction and DCIS use (NSABP P-1).
Q17. A postmenopausal woman with hormone-receptor-positive early breast cancer is given adjuvant letrozole. Letrozole is
(a) a GnRH agonist
(b) a SERM
(c) an aromatase inhibitor
(d) a progestin
Show answer
Answer: (c) — Femara label.
Q18. A woman on clomiphene for ovulation induction develops abdominal pain and distension, nausea and weight gain. Suspect
(a) appendicitis
(b) ovarian hyperstimulation syndrome
(c) ectopic pregnancy only
(d) fibroid
Show answer
Answer: (b) — Clomiphene also causes visual blurring or flashes.
Q19. A 17-year-old asks to use Depo-Provera injections for 4 years. The label warns of
(a) lactic acidosis
(b) hyperkalaemia
(c) loss of bone mineral density; not beyond 2 years unless other methods are unsuitable
(d) endometrial cancer
Show answer
Answer: (c) — Boxed warning.
Q20. A woman starting alendronate asks how to take it. Correct advice:
(a) with milk at bedtime
(b) with food to avoid nausea
(c) lying down to absorb better
(d) with plain water, 30 minutes before the first food or drink, and stay upright 30 minutes
Show answer
Answer: (d) — Fosamax label.
Q21. After 6 years of alendronate, a woman develops new thigh pain with minimal trauma. Suspect
(a) muscle strain only
(b) gout
(c) an atypical femur fracture
(d) DVT
Show answer
Answer: (c) — Evaluate new thigh or groin pain; also watch for osteonecrosis of the jaw.
Q22. A dialysis patient with osteoporosis is given denosumab. The boxed risk is
(a) hypercalcaemia
(b) agranulocytosis
(c) severe hypocalcaemia
(d) QT prolongation
Show answer
Answer: (c) — Advanced CKD (eGFR < 30) including dialysis.
Q23. Denosumab works by inhibiting
(a) aromatase
(b) osteoclast H+ pump
(c) RANK ligand (RANKL)
(d) PTH receptor
Show answer
Answer: (c) — Prolia label.
Q24. In ICMR's hypothyroidism workflow, a young patient's target TSH on treatment is
(a) < 0.1 mU/L
(b) 5–10 mU/L
(c) 1–2.5 mU/L
(d) 10–20 mU/L
Show answer
Answer: (c) — Middle-aged 1.5–3 mU/L.
Active Recall
From memory: give ICMR's levothyroxine starting doses for primary, elderly or cardiac, congenital and central hypothyroidism; compare methimazole and propylthiouracil; list corticosteroid adverse effects and why tapering matters; and give the key warning for estrogen, raloxifene, tamoxifen, letrozole, clomiphene, DMPA, alendronate and denosumab.