Asthma, COPD and Cough Drugs for NEET PG Pharmacology: GINA 2026, GOLD 2026, ICMR Protocols, Salbutamol, ICS, Theophylline
Start Here
🎯 Exam priority: High. Expect: why SABA alone is no longer advised, the GINA reliever, acute severe asthma management, COPD initial therapy, theophylline toxicity with ciprofloxacin, montelukast's boxed warning and tiotropium in a man with BPH.
CBME mapping: PH 5.1–5.2. India's ICMR asthma and COPD workflows date from October 2019; the international updates used here are GINA 2026 and GOLD 2026. Where they differ, both are shown.
Asthma: ICMR Steps and GINA 2026
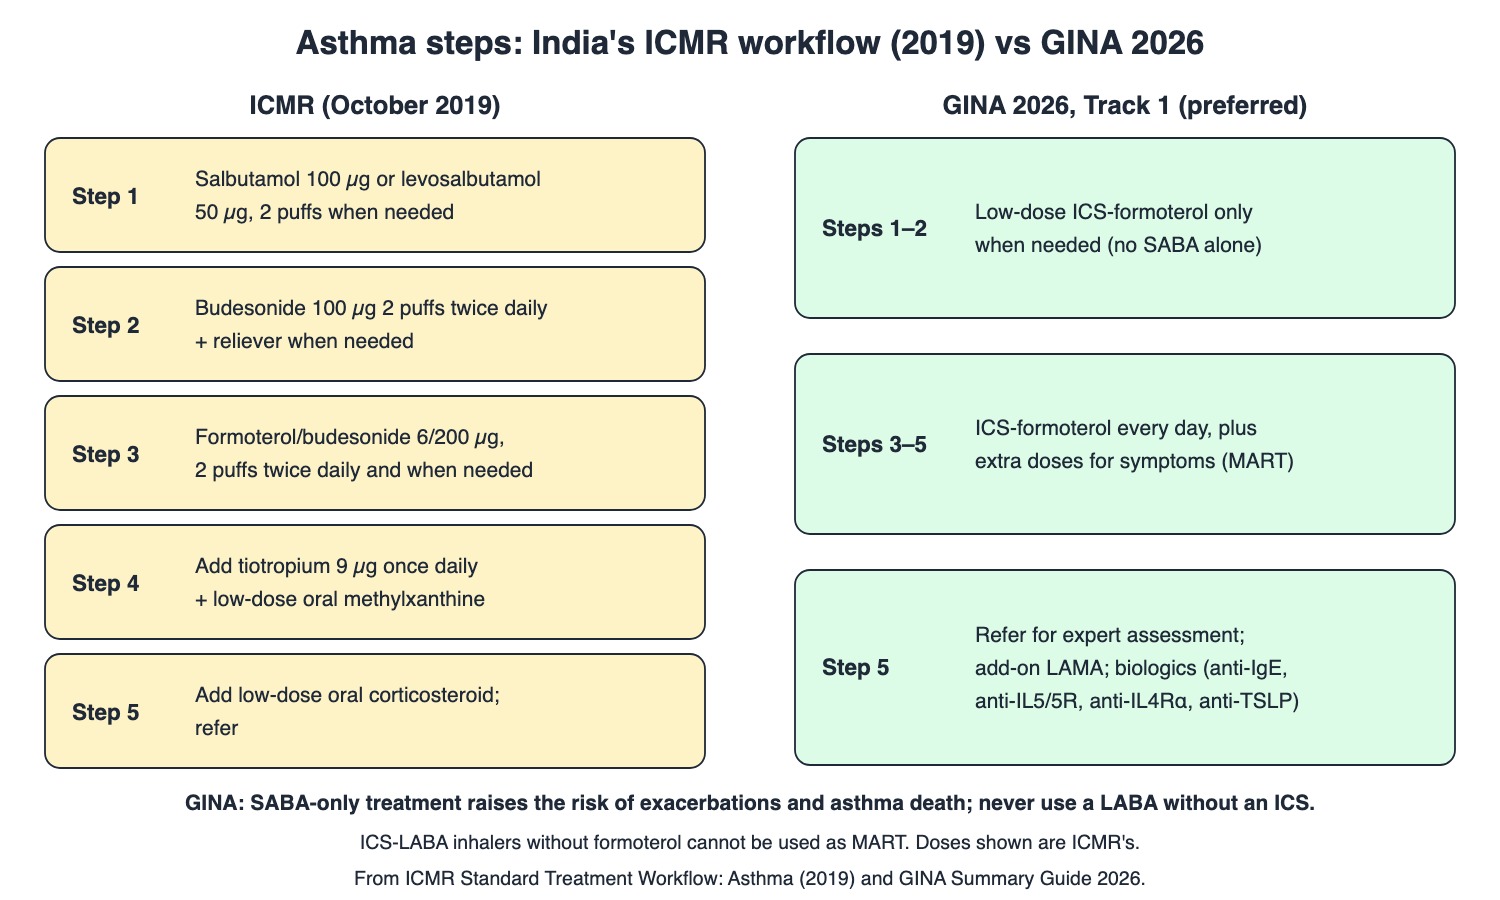
Asthma step therapy: the ICMR workflow (2019) beside GINA 2026 Track 1. Drawn by TrackNation.
GINA 2026: SABA-only treatment is linked to more exacerbations, worse lung function and more asthma deaths, so everyone with asthma gets an inhaled steroid. Steps 1–2: low-dose ICS-formoterol only when needed. Steps 3–5: ICS-formoterol daily plus extra doses for symptoms (MART); only formoterol-containing inhalers can be used this way.
ICMR (2019): still starts with salbutamol or levosalbutamol alone when needed, then adds budesonide, then formoterol/budesonide, then tiotropium + a low-dose methylxanthine, then a low-dose oral steroid.
A LABA must never be used without an ICS in asthma.
Acute Severe Asthma (ICMR)
Admit if the patient cannot complete sentences, is agitated, uses accessory muscles, has RR > 30, HR > 110, pulsus paradoxus > 25 mm Hg, a silent chest or room-air SpO2 < 92%.
Treat: oxygen to SpO2 92–95%; nebulised levosalbutamol/ipratropium (1.25/0.5 mg) three doses 20 minutes apart; IV hydrocortisone 200 mg, then oral prednisolone 0.5 mg/kg daily for 5 days.
Life-threatening (altered sensorium, cyanosis, paradoxical breathing, hypotension, HR < 60): refer at once to an ICU.
GINA oral steroid doses: adults prednisolone 40–50 mg daily for 5–7 days; children 1–2 mg/kg/day (maximum 40 mg) for 3–5 days.
COPD: ICMR and GOLD 2026
Diagnosis: post-bronchodilator FEV1/FVC < 0.70. First advice: stop smoking.
ICMR: mild — levosalbutamol when needed; moderate — tiotropium 9 µg 2 puffs daily + levosalbutamol; severe — formoterol/budesonide 6/200 µg 2 puffs twice daily.
GOLD 2026: group A — a bronchodilator; group B — LABA+LAMA; group E — LABA+LAMA, adding an ICS if eosinophils ≥ 300/µL. Still exacerbating: azithromycin (non-smokers; mind resistance) or roflumilast (chronic bronchitis with a past severe exacerbation). LABA+ICS carries a higher pneumonia risk than LABA+LAMA. IV theophylline is not advised for exacerbations.
ICMR exacerbation: more bronchodilator; amoxicillin, azithromycin or doxycycline for 5 days; prednisolone 30 mg for 5 days; oxygen to SpO2 about 92%.
The Drugs
Drug | How it works (label) | Exam points (label) |
Salbutamol, levosalbutamol | Short-acting beta2-agonist | Paradoxical bronchospasm; hypokalaemia, glucose changes |
Formoterol (with an ICS) | Long-acting beta2-agonist | LABA alone raises asthma-related death (class effect): always with ICS |
Budesonide (inhaled) | Corticosteroid | Oral and throat candidiasis; use a spacer with a pMDI (GINA) |
Montelukast | Blocks the CysLT1 leukotriene receptor | Boxed: serious neuropsychiatric events |
Tiotropium, ipratropium | Muscarinic antagonists | Not a rescue drug (tiotropium); worsens narrow-angle glaucoma, urinary retention |
Theophylline | Inhibits PDE III/IV; blocks adenosine receptors | Range 10–20 mcg/mL; cimetidine, ciprofloxacin raise levels (CYP1A2); vomiting, arrhythmias, seizures |
Omalizumab | Anti-IgE antibody | Boxed: anaphylaxis |
Roflumilast | PDE4 inhibitor (oral) | Weight loss; depression or suicidal thoughts |
Codeine | Opioid (cough, pain) | Contraindicated under 12, and under 18 after tonsillectomy (CYP2D6 ultra-rapid metabolisers) |
Traps the Examiner Sets
GINA: no SABA-only treatment; the reliever is as-needed low-dose ICS-formoterol.
Salmeterol-fluticasone cannot be used as MART (no formoterol).
Theophylline toxicity after ciprofloxacin or cimetidine.
Tiotropium is not a reliever; caution in glaucoma and BPH.
COPD with high eosinophils (≥ 300) benefits from adding an ICS.
Memory Hooks & Shortcuts
Shortcuts to lock in this article's numbers and lists. Each one only re-packages facts proven above.
🧠 No SABA Solo — GINA: every asthmatic gets an inhaled steroid
🧠 Formoterol is the MART-ian — only ICS-formoterol inhalers work as maintenance and reliever
🧠 LABA needs a BUDdy (ICS) — never a LABA alone
🧠 Theophylline's CC enemies: Cimetidine, Ciprofloxacin — they raise theophylline levels
🧠 Tio Ties up the bladder — urinary retention with tiotropium
🧠 GOLD E: 300 eos earns the steroid — add ICS if eosinophils ≥ 300
Rapid-Revision Cards
GINA: SABA alone?
No; raises exacerbations and asthma deaths.
GINA Steps 1–2
As-needed low-dose ICS-formoterol.
MART
ICS-formoterol daily + as reliever; formoterol only.
LABA rule
Never without ICS in asthma.
ICMR asthma steps
SABA → +budesonide → formoterol/budesonide → +tiotropium, methylxanthine → +oral steroid.
Severe acute asthma (ICMR)
Can't finish sentences, RR > 30, HR > 110, SpO2 < 92%: admit.
Acute asthma treatment (ICMR)
O2 92–95%, nebulised levosalbutamol/ipratropium ×3, IV hydrocortisone 200 mg.
Life-threatening asthma
Drowsy, cyanosis, paradoxical breathing, HR < 60: ICU.
Prednisolone (GINA)
Adult 40–50 mg 5–7 d; child 1–2 mg/kg (max 40) 3–5 d.
Salbutamol AEs
Hypokalaemia, glucose change, paradoxical bronchospasm.
ICS AE
Oral candidiasis; spacer.
Montelukast
CysLT1 blocker; boxed neuropsychiatric.
Tiotropium
Not rescue; glaucoma, urinary retention.
Theophylline
PDE III/IV + adenosine block; 10–20 mcg/mL.
Theophylline interactions
Cimetidine, ciprofloxacin ↑ levels (CYP1A2).
Omalizumab
Anti-IgE; anaphylaxis.
COPD diagnosis
Post-BD FEV1/FVC < 0.70.
GOLD A / B
Bronchodilator / LABA+LAMA.
GOLD E
LABA+LAMA; + ICS if eos ≥ 300.
COPD add-ons
Azithromycin (non-smokers), roflumilast (chronic bronchitis).
Roflumilast
PDE4; weight loss, depression.
ICMR COPD exacerbation
Antibiotic 5 d + prednisolone 30 mg 5 d; O2 ~92%.
Codeine
Not < 12 y, or < 18 y after tonsillectomy.
Sources
Facts in this article were checked against these documents.
Standard Treatment Workflows: Asthma; Chronic Obstructive Pulmonary Disease — Indian Council of Medical Research / Department of Health Research, MoHFW, October 2019
Summary Guide for Asthma Management and Prevention — Global Initiative for Asthma (GINA), 2026 (link)
Global Strategy for Prevention, Diagnosis and Management of COPD: 2026 Report — Global Initiative for Chronic Obstructive Lung Disease (GOLD), 2026 (link)
Prescribing labels: Ventolin HFA, Symbicort, Pulmicort Flexhaler, Singulair, Spiriva Respimat, theophylline ER, Xolair, Daliresp, codeine sulfate — DailyMed, US National Library of Medicine, current labels, accessed November 2026 (link)
Competency Based Undergraduate Curriculum, Pharmacology (PH 5.1–5.2) — National Medical Commission, 2024
Test Yourself: Practice Questions
Twenty-four questions in NEET PG style, most of them clinical vignettes.
Practice Questions (NEET PG pattern)
Original questions written in the style of the exam: +4 for a correct answer, −1 for a wrong one. Every answer was checked against the sources listed above. NEET PG papers are not published by NBEMS, so these are not past-paper questions.
Q1. A 24-year-old with newly diagnosed mild asthma has symptoms once a week. Under GINA 2026, the preferred treatment is
(a) low-dose ICS-formoterol taken only when needed
(b) a LABA alone
(c) oral theophylline
(d) salbutamol alone when needed
Show answer
Answer: (a) — GINA Steps 1–2: as-needed low-dose ICS-formoterol; SABA-only treatment is not advised.
Q2. GINA advises against treating asthma with a SABA alone because SABA-only treatment
(a) is too expensive
(b) is linked to more exacerbations and more asthma deaths
(c) causes hyperkalaemia
(d) causes oral candidiasis
Show answer
Answer: (b) — SABA-only treatment: more exacerbations, worse lung function, more asthma deaths.
Q3. A patient asks to use salmeterol alone for asthma. The correct reply is
(a) it is the preferred first step
(b) it is fine if symptoms are mild
(c) a LABA must not be used without an inhaled corticosteroid
(d) it replaces the ICS
Show answer
Answer: (c) — GINA; LABA monotherapy raises asthma-related death (class effect, Symbicort label).
Q4. An asthmatic on step-3 therapy is to be put on maintenance-and-reliever therapy (MART). Which inhaler can be used?
(a) Tiotropium alone
(b) Fluticasone-salmeterol
(c) Budesonide-formoterol
(d) Salbutamol alone
Show answer
Answer: (c) — Only ICS-formoterol inhalers can be used as MART.
Q5. A woman with asthma cannot complete sentences; RR 34, HR 118, room-air SpO2 89%. Per ICMR she should be
(a) sent home on inhalers
(b) given oral montelukast only
(c) admitted as severe acute asthma
(d) given a LABA alone
Show answer
Answer: (c) — Admit if unable to complete sentences, RR > 30, HR > 110, silent chest or SpO2 < 92%.
Q6. In that patient, the ICMR initial drug treatment is
(a) oral theophylline
(b) IV magnesium alone
(c) montelukast and cetirizine
(d) nebulised levosalbutamol/ipratropium three times 20 minutes apart, plus IV hydrocortisone 200 mg
Show answer
Answer: (d) — Also oxygen to SpO2 92–95%, then oral prednisolone 0.5 mg/kg for 5 days.
Q7. During an asthma attack a patient becomes drowsy, cyanosed, with paradoxical breathing and HR 52. ICMR advises
(a) stopping oxygen
(b) oral prednisolone and discharge
(c) immediate referral to a centre with an ICU
(d) outpatient follow-up in a week
Show answer
Answer: (c) — Life-threatening features: altered sensorium, cyanosis, paradoxical breathing, hypotension, bradycardia < 60.
Q8. GINA's oral prednisolone course for an adult with a moderate asthma exacerbation is
(a) 10 mg for 6 weeks
(b) 5 mg for 1 day
(c) 1 g IV for 3 days
(d) 40–50 mg each morning for 5–7 days
Show answer
Answer: (d) — Children: 1–2 mg/kg/day up to 40 mg for 3–5 days.
Q9. Repeated salbutamol nebulisation in the emergency room can cause
(a) hypokalaemia
(b) hyperkalaemia
(c) hypercalcaemia
(d) hyponatraemia
Show answer
Answer: (a) — Ventolin label: hypokalaemia and glucose changes; also paradoxical bronchospasm.
Q10. A child using an inhaled budesonide pMDI without a spacer develops oral thrush. The cause and prevention are
(a) vitamin deficiency; add B12
(b) aphthous ulcers; stop the ICS
(c) oral candidiasis; use a spacer
(d) leukoplakia; biopsy
Show answer
Answer: (c) — Pulmicort label: Candida infection of mouth and throat; GINA: ICS by pMDI should be used with a spacer.
Q11. A 15-year-old on montelukast becomes withdrawn with suicidal thoughts. The label's boxed warning covers
(a) hepatotoxicity
(b) serious neuropsychiatric events
(c) anaphylaxis
(d) QT prolongation
Show answer
Answer: (b) — Singulair boxed warning.
Q12. Montelukast works by
(a) binding IgE
(b) stimulating beta2 receptors
(c) inhibiting 5-lipoxygenase
(d) blocking the CysLT1 leukotriene receptor
Show answer
Answer: (d) — Selective cysteinyl leukotriene CysLT1 receptor antagonist.
Q13. A 70-year-old with COPD and prostatic enlargement starts tiotropium. The label warns about
(a) lupus
(b) gynaecomastia
(c) hypoglycaemia
(d) worsening urinary retention (and narrow-angle glaucoma)
Show answer
Answer: (d) — Muscarinic antagonist: caution in BPH, bladder-neck obstruction and narrow-angle glaucoma; not a rescue drug.
Q14. A man on theophylline is given ciprofloxacin for a UTI and develops vomiting, palpitations and a seizure. The reason is
(a) an allergic reaction
(b) ciprofloxacin causes hypokalaemia only
(c) ciprofloxacin reduces theophylline clearance (CYP1A2), causing toxicity
(d) theophylline induces ciprofloxacin
Show answer
Answer: (c) — Like cimetidine, ciprofloxacin inhibits CYP1A2; theophylline toxicity: vomiting, arrhythmias, seizures. Range 10–20 mcg/mL.
Q15. Theophylline's bronchodilator effect is attributed mainly to
(a) beta2 stimulation
(b) inhibition of phosphodiesterase (PDE III and IV)
(c) leukotriene blockade
(d) muscarinic blockade
Show answer
Answer: (b) — Label: PDE III and, to a lesser extent, PDE IV; some adverse effects come from adenosine receptor antagonism.
Q16. Omalizumab, used in severe allergic asthma, carries a boxed warning for
(a) agranulocytosis
(b) hypokalaemia
(c) anaphylaxis
(d) hepatic failure
Show answer
Answer: (c) — Xolair is an anti-IgE antibody.
Q17. A 60-year-old smoker has chronic cough and breathlessness. COPD is confirmed by
(a) chest X-ray hyperinflation
(b) FEV1 < 80% before bronchodilator
(c) sputum culture
(d) post-bronchodilator FEV1/FVC < 0.70
Show answer
Answer: (d) — GOLD 2026 and ICMR.
Q18. A newly diagnosed COPD patient with significant breathlessness but no exacerbations (GOLD group B) should start
(a) an ICS alone
(b) a SABA alone
(c) oral theophylline
(d) a LABA+LAMA combination
Show answer
Answer: (d) — GOLD 2026 group B.
Q19. A COPD patient with two exacerbations last year has blood eosinophils of 400/µL. GOLD suggests considering initial
(a) roflumilast alone
(b) LABA+LAMA+ICS
(c) no treatment
(d) SABA alone
Show answer
Answer: (b) — Group E: consider LABA+LAMA+ICS if eosinophils ≥ 300/µL.
Q20. Per ICMR, a patient with moderate COPD is started on
(a) oral prednisolone daily
(b) salbutamol tablets
(c) tiotropium 9 µg 2 puffs once daily plus levosalbutamol when needed
(d) montelukast
Show answer
Answer: (c) — ICMR COPD workflow.
Q21. A COPD patient with chronic bronchitis and a past hospital admission for exacerbation keeps exacerbating on triple therapy. GOLD suggests adding
(a) roflumilast
(b) a SABA only
(c) IV theophylline
(d) a second LABA
Show answer
Answer: (a) — Roflumilast (PDE4 inhibitor): watch weight loss and depression.
Q22. A patient started on roflumilast loses weight unexpectedly. The label advises
(a) ignoring it
(b) doubling the dose
(c) adding theophylline
(d) evaluating the weight loss and considering stopping it
Show answer
Answer: (d) — Daliresp label.
Q23. For a COPD exacerbation at a health centre, ICMR lists
(a) an antibiotic (amoxicillin, azithromycin or doxycycline) and prednisolone 30 mg for 5 days
(b) long-term oral steroids
(c) montelukast
(d) IV theophylline
Show answer
Answer: (a) — Plus more bronchodilator; GOLD does not recommend IV methylxanthines.
Q24. A 9-year-old has a cough after tonsillectomy. Codeine is
(a) contraindicated (under 12, and under 18 after tonsillectomy)
(b) safe in low dose
(c) safe after age 6
(d) first choice
Show answer
Answer: (a) — CYP2D6 ultra-rapid metabolisers can make dangerous amounts of morphine.
Active Recall
From memory: compare the ICMR asthma steps with GINA 2026 Track 1, give the ICMR criteria and treatment for acute severe asthma, outline COPD treatment under ICMR and GOLD 2026, and give the mechanism and key adverse effects of salbutamol, inhaled steroids, montelukast, tiotropium, theophylline, omalizumab and roflumilast.