Genital Infections and PID for NEET PG OBG: Vaginal Discharge Types, Amsel Criteria, NACO 2024 Colour Kits and Management of PID
Start Here
🎯 Exam priority: High. Expect: telling BV, trichomonas and candida apart from the discharge and pH, Amsel criteria, single-dose treatments, who needs partner treatment, NACO colour-coded kits, PID signs, complications and treatment, IUD in PID, and drugs to avoid in pregnancy.
CBME mapping: OG27. Indian anchor: NACO National Technical Guidelines on STI and RTI (2024). Syphilis and HIV in pregnancy are in OBG 09; genital ulcers and skin STIs are in Dermatology 12.
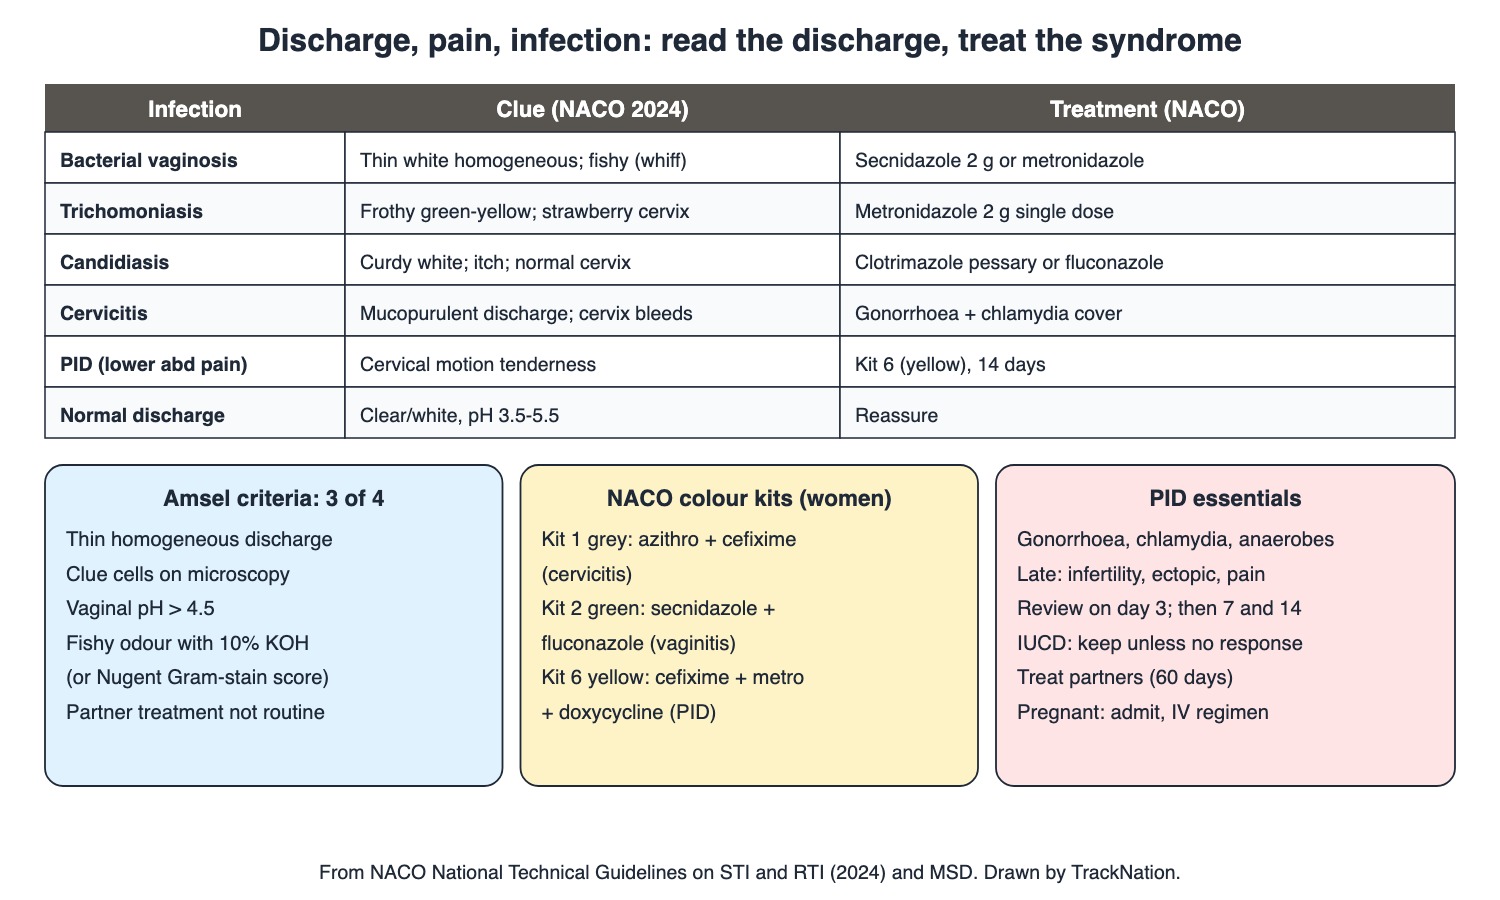
Discharge types, Amsel criteria, NACO kits and PID essentials. Drawn by TrackNation.
Vaginal Discharge (NACO 2024, MSD)
Normal discharge: clear/white, little odour, pH 3.5–5.5 (NACO); lactobacilli keep the pH acidic (MSD: generally <4.5).
Bacterial vaginosis — the commonest infectious vaginitis: lactobacilli replaced by Gardnerella, Mobiluncus, Mycoplasma hominis and anaerobes. Thin, white, homogeneous discharge; cervix normal. Amsel — 3 of 4: homogeneous discharge, clue cells, pH >4.5, fishy odour with 10% KOH (whiff test); or Nugent Gram-stain score. In pregnancy linked to PROM, chorioamnionitis and preterm birth. Routine partner treatment not recommended; avoid douching.
Trichomoniasis: frothy greenish-yellow discharge, vulval redness, strawberry cervix (punctate haemorrhages). Metronidazole 2 g single dose (or secnidazole/tinidazole 2 g); treat the partner; no alcohol during and for 48 h after metronidazole.
Candidiasis: thick, white, curdy, itchy; normal cervix. Risks: diabetes, antibiotics, steroids, pregnancy, immunosuppression. KOH mount shows hyphae and spores. Clotrimazole pessary or fluconazole 150 mg; partner infection is rare.
Cervicitis (gonorrhoea, chlamydia): mucopurulent discharge, cervix bleeds on touch. Gonorrhoea: ceftriaxone 500 mg IM (or cefixime 800 mg); chlamydia: doxycycline 100 mg twice daily × 7 days (azithromycin 1 g in pregnancy — doxycycline and quinolones are contraindicated in pregnancy).
Syndromic Management and NACO Kits
Kit 1 (grey): azithromycin 1 g + cefixime 800 mg — urethral discharge, vaginal discharge (cervicitis), scrotal swelling, presumptive treatment.
Kit 2 (green): secnidazole 2 g + fluconazole 150 mg — vaginal discharge (vaginitis: BV, trichomonas, candida).
Kit 6 (yellow): cefixime 800 mg + metronidazole 400 mg BD × 14 days + doxycycline 100 mg BD × 14 days — lower abdominal pain / PID.
Every STI visit: offer HIV and syphilis testing, condoms, counselling and partner management.
Pelvic Inflammatory Disease (MSD, NACO)
PID = polymicrobial infection of the upper genital tract (gonorrhoea, chlamydia, anaerobes); tubo-ovarian abscess may form. Signs: fever, lower abdominal pain, mucopurulent discharge, cervical motion tenderness.
Long-term: infertility, ectopic pregnancy, chronic pelvic pain. Fitz-Hugh–Curtis perihepatitis can mimic cholecystitis.
Red flags needing referral (NACO): missed/overdue period, recent delivery/abortion, guarding or rebound, abnormal bleeding, mass. Pregnant women with PID: admit for a parenteral regimen safe in pregnancy.
Mild–moderate PID is treated as outpatient (Kit 6, or ceftriaxone 500 mg IM + doxycycline + metronidazole for 14 days). Review at 3 days, then days 7 and 14; no improvement → admit.
IUCD: PID risk is mainly in the first 3 weeks; the device need not be removed unless there is no improvement in 48–72 hours. Treat male partners from the previous 60 days.
Traps the Examiner Sets
BV: treat the woman, not routinely the partner; trichomonas: treat both.
pH >4.5 points to BV; candida keeps the pH below 4.5.
Doxycycline and quinolones are avoided in pregnancy.
PID with an IUCD: treat first; remove only if no response in 48–72 h.
Memory Hooks & Shortcuts
Shortcuts to lock in this article's numbers and lists. Each one only re-packages facts proven above.
🧠 Discharge colours: 'BV is grey-white and fishy, Trich is green and frothy, Candida is white and curdy' — discharge
🧠 Amsel '3 of 4: Thin, Clue, pH > 4.5, Whiff' — Amsel
🧠 NACO kits for women: '1 Grey for the cervix, 2 Green for the vagina, 6 Yellow for the pelvis' — kits
🧠 Partners: 'Trich — treat both; BV and Candida — just her' — partners
🧠 PID follow-up '3-7-14' — PID
Rapid-Revision Cards
Normal discharge pH
3.5–5.5 (NACO).
Commonest vaginitis
BV.
BV discharge
Thin, white, homogeneous, fishy.
Amsel
3 of 4: discharge, clue cells, pH >4.5, whiff.
BV partner
Not routinely.
BV in pregnancy
PROM, preterm birth.
Trichomonas
Frothy green; strawberry cervix.
TV treatment
Metronidazole 2 g stat + partner.
Metronidazole
No alcohol + 48 h.
Candida
Curdy white, itchy; KOH hyphae.
Candida risks
Diabetes, antibiotics, steroids, pregnancy.
Gonorrhoea
Ceftriaxone 500 mg IM.
Chlamydia
Doxycycline 7 d (azithro in pregnancy).
Kit 1 grey
Azithro + cefixime (cervicitis).
Kit 2 green
Secnidazole + fluconazole.
Kit 6 yellow
PID, 14 days.
PID complications
Infertility, ectopic, pain.
Fitz-Hugh–Curtis
Perihepatitis.
PID review
Day 3, 7, 14.
PID + IUCD
Keep unless no response 48–72 h.
PID partners
Last 60 days.
Sources
Facts in this article were checked against these documents.
National Technical Guidelines on STI and RTI — National AIDS Control Organisation, MoHFW, 2024
MSD Manual Professional: Overview of Vaginitis; Bacterial Vaginosis; Candidal Vaginitis; Pelvic Inflammatory Disease — Merck & Co. (MSD Manuals), 2024–26 (link)
Competency Based Undergraduate Curriculum, Vol III: Obstetrics & Gynaecology (OG27) — National Medical Commission, 2024
Test Yourself: Practice Questions
Thirty questions in NEET PG style, most of them clinical vignettes.
Practice Questions (NEET PG pattern)
Original questions written in the style of the exam: +4 for a correct answer, −1 for a wrong one. Every answer was checked against the sources listed above. NEET PG papers are not published by NBEMS, so these are not past-paper questions.
Q1. Normal vaginal discharge per NACO has a pH of
(a) above 7
(b) 6.5–7.5
(c) 3.5–5.5
(d) below 2
Show answer
Answer: (c) — Lactobacilli.
Q2. The commonest infectious cause of vaginitis is
(a) trichomoniasis
(b) bacterial vaginosis
(c) gonorrhoea
(d) candidiasis
Show answer
Answer: (b) — MSD.
Q3. A woman has a thin, white, homogeneous discharge with a fishy smell; pH 5.0. Diagnosis:
(a) trichomoniasis
(b) physiological discharge
(c) candidiasis
(d) bacterial vaginosis
Show answer
Answer: (d) — Amsel.
Q4. Amsel's criteria require how many of the four features?
(a) 4
(b) 2
(c) 1
(d) 3
Show answer
Answer: (d) — NACO.
Q5. Clue cells are
(a) budding yeast
(b) motile flagellates
(c) pus cells
(d) squamous cells covered with coccobacilli
Show answer
Answer: (d) — BV.
Q6. The whiff test is positive when
(a) the discharge froths
(b) a fishy odour appears on adding 10% KOH
(c) hyphae are seen
(d) the pH is below 4
Show answer
Answer: (b) — BV.
Q7. For a single episode of BV, the male partner should
(a) always get metronidazole
(b) not routinely be treated
(c) get fluconazole
(d) be tested for HIV only
Show answer
Answer: (b) — Consider if recurrent.
Q8. BV in pregnancy is associated with
(a) post-term pregnancy
(b) PROM, chorioamnionitis and preterm birth
(c) macrosomia
(d) pre-eclampsia
Show answer
Answer: (b) — MSD.
Q9. A woman has frothy greenish-yellow discharge and punctate haemorrhages on the cervix. Diagnosis:
(a) gonorrhoea
(b) candidiasis
(c) trichomoniasis
(d) BV
Show answer
Answer: (c) — Strawberry cervix.
Q10. First-line single-dose treatment for trichomoniasis (NACO) is
(a) azithromycin 1 g
(b) ceftriaxone 500 mg
(c) fluconazole 150 mg
(d) metronidazole 2 g orally
Show answer
Answer: (d) — Treat partner.
Q11. A woman on metronidazole should avoid alcohol during treatment and for
(a) no restriction
(b) 48 hours after
(c) 2 weeks after
(d) 6 months after
Show answer
Answer: (b) — Disulfiram-like.
Q12. A diabetic woman on antibiotics has intense itching and thick curdy white discharge; cervix normal. Diagnosis:
(a) trichomoniasis
(b) candidiasis
(c) BV
(d) cervicitis
Show answer
Answer: (b) — KOH: hyphae.
Q13. The bedside test that best shows Candida is
(a) 10% KOH wet mount for hyphae and spores
(b) pH strip only
(c) whiff test
(d) Gram stain for diplococci
Show answer
Answer: (a) — MSD.
Q14. In vulvovaginal candidiasis, the sexual partner
(a) rarely has infection; routine treatment is not needed
(b) always needs treatment
(c) must avoid sex for 6 months
(d) needs metronidazole
Show answer
Answer: (a) — MSD.
Q15. NACO Kit 2 (green) for vaginitis contains
(a) azithromycin + cefixime
(b) secnidazole 2 g + fluconazole 150 mg
(c) cefixime + metronidazole + doxycycline
(d) benzathine penicillin + azithromycin
Show answer
Answer: (b) — BV/TV/candida.
Q16. NACO Kit 1 (grey) is used for vaginal discharge syndrome due to
(a) cervicitis
(b) genital ulcer
(c) PID
(d) vaginitis
Show answer
Answer: (a) — Azithromycin + cefixime.
Q17. NACO Kit 6 (yellow) is for
(a) lower abdominal pain / PID
(b) urethral discharge
(c) genital herpes
(d) inguinal bubo
Show answer
Answer: (a) — 14 days.
Q18. A woman with mucopurulent discharge has a cervix that bleeds on touch. Suspect
(a) candidiasis
(b) cervicitis (gonorrhoea/chlamydia)
(c) BV
(d) physiological ectropion only
Show answer
Answer: (b) — NACO.
Q19. First-line treatment of gonorrhoea (NACO 2024) is
(a) penicillin G
(b) ceftriaxone 500 mg IM single dose
(c) ciprofloxacin 500 mg
(d) doxycycline alone
Show answer
Answer: (b) — Cefixime substitute.
Q20. A pregnant woman has chlamydial cervicitis. Avoid
(a) doxycycline and quinolones
(b) azithromycin
(c) amoxicillin
(d) erythromycin
Show answer
Answer: (a) — Use azithromycin.
Q21. PID is best defined as
(a) a lower vaginal infection only
(b) a viral infection
(c) a fungal infection
(d) a polymicrobial infection of the upper female genital tract
Show answer
Answer: (d) — MSD.
Q22. A young woman has fever, lower abdominal pain and cervical motion tenderness. Likely
(a) PID
(b) BV
(c) candidiasis
(d) cervical ectropion
Show answer
Answer: (a) — Kit 6.
Q23. A long-term complication of PID is
(a) PCOS
(b) endometrial cancer
(c) fibroids
(d) tubal infertility and ectopic pregnancy
Show answer
Answer: (d) — Also chronic pain.
Q24. A woman with PID has right upper quadrant pain mimicking cholecystitis. This is
(a) Mittelschmerz
(b) Asherman syndrome
(c) Meigs syndrome
(d) Fitz-Hugh–Curtis syndrome
Show answer
Answer: (d) — Perihepatitis.
Q25. A woman with lower abdominal pain has missed her period. NACO advises
(a) refer immediately — red flag
(b) reassure
(c) give Kit 6 and review in 2 weeks
(d) give Kit 2
Show answer
Answer: (a) — Rule out ectopic.
Q26. A pregnant woman is suspected to have PID. Management:
(a) admit for a parenteral regimen safe in pregnancy
(b) no treatment till delivery
(c) doxycycline orally
(d) outpatient Kit 6
Show answer
Answer: (a) — NACO.
Q27. After starting outpatient PID treatment, the first review per NACO is at
(a) 3 months
(b) no review
(c) 3 weeks
(d) 3 days
Show answer
Answer: (d) — Then days 7 and 14.
Q28. A woman with an IUCD is diagnosed with PID. NACO advises
(a) treat and keep the IUCD; remove only if no improvement in 48–72 h
(b) give a second IUCD
(c) remove the IUCD at once
(d) never treat while IUCD in place
Show answer
Answer: (a) — Close follow-up.
Q29. The PID risk attributable to an IUCD is mainly in the first
(a) 3 years
(b) day of removal
(c) menopause
(d) 3 weeks after insertion
Show answer
Answer: (d) — NACO.
Q30. Male partners of a woman with PID should be examined and treated if they had sexual contact in the preceding
(a) 60 days
(b) 7 days
(c) 24 hours
(d) 1 year
Show answer
Answer: (a) — NACO.
Active Recall
From memory: describe normal discharge and the features, tests and treatment of BV, trichomoniasis, candidiasis and cervicitis, list the NACO kits for women, and outline the diagnosis, complications, treatment and follow-up of PID including IUCD users and partners.